ADHD and Hormones in Women: Cycle, PMDD & Menopause
By Kristen McClure, MSW, LCSW | Neurodivergent-affirming therapy for women
You have been managing your ADHD — maybe for years, maybe your whole life. Then something shifts.
Your symptoms feel worse for a week every month. Or you reach your late thirties or forties and everything that used to work stops working. Or you have a baby and suddenly you cannot function the way you did before.
And nobody connects the dots.
Not your prescriber. Not your OB. Not the therapist you saw years ago.
This is one of the most common and most underdiscussed experiences for women with ADHD.
Hormones do not cause ADHD. But they can affect how ADHD shows up.
Estrogen and progesterone interact with brain systems involved in attention, mood, and cognition, including dopamine pathways that are relevant to ADHD. The research is still limited, but growing evidence suggests that menstrual-cycle changes, postpartum shifts, and the transition through perimenopause and menopause can change how ADHD symptoms are experienced.
Sometimes the change is dramatic.
If your ADHD symptoms reliably change before your period, postpartum, or during perimenopause, that pattern is worth taking seriously and tracking. Hormonal shifts may be one contributor, alongside sleep, stress, illness, pain, sensory load, and changes in daily demands.
How Estrogen and Progesterone May Affect ADHD
To understand why hormones matter for ADHD, it helps to understand one key relationship:
Estrogen interacts with dopamine and other brain systems involved in attention, motivation, memory, and emotion. Dopamine signaling is also one of the systems implicated in ADHD.
Newer research suggests that changes in estrogen and progesterone may influence ADHD symptoms and cognitive functioning across the menstrual cycle and other hormonal transitions. The exact mechanisms are still being worked out. It is more accurate to say that ovarian hormones interact with brain systems relevant to ADHD than to reduce the pattern to a simple "more estrogen equals more dopamine" explanation.
Anecdotally, many ADHD women report that some parts of the cycle feel easier: focus may feel steadier, emotional regulation may take less effort, and tasks may be easier to start. Newer research is beginning to document cycle-related symptom changes, but the pattern is not identical for every woman.
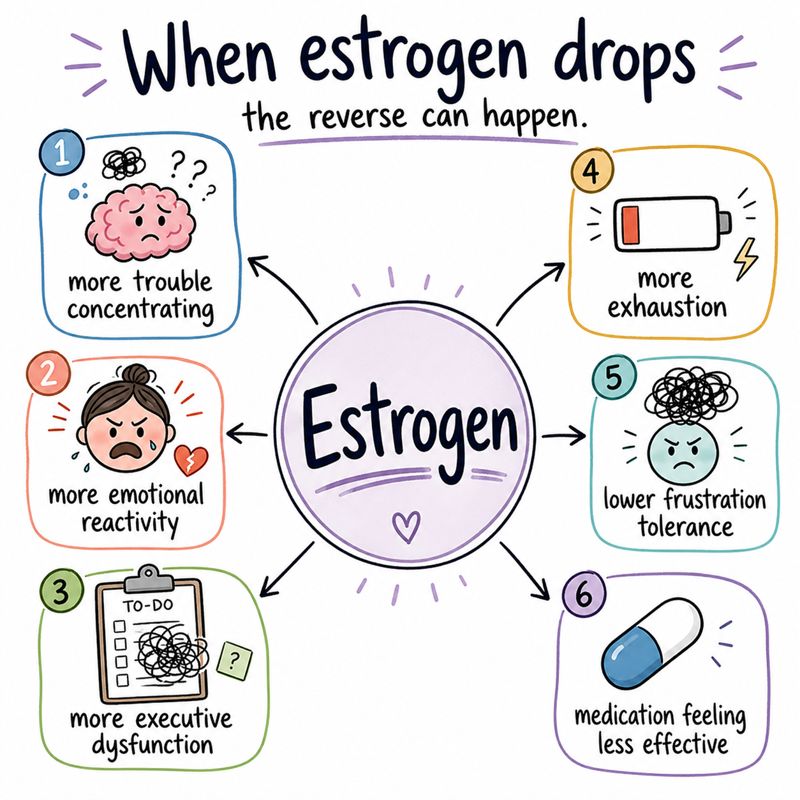
For some women, the premenstrual phase is when the opposite pattern shows up and ADHD-related difficulties become more noticeable.
- You may notice:
This is not simply a personality issue or a lack of trying. Anecdotally, women often describe real changes in focus, emotional regulation, energy, and executive functioning across hormonal shifts, and newer research is beginning to support those reports.
The research is still developing. ADHD research has historically focused more on boys and men, and the specific estrogen-dopamine connection in ADHD women is still not fully mapped.
In lived experience and anecdotal reports, women have been describing these shifts for years. Newer research is beginning to support the pattern, while also showing that symptom changes vary substantially from person to person.
For some ADHD women, hormonal transitions can change capacity enough that previously manageable demands become much harder.
ADHD and the Menstrual Cycle
Many women with ADHD describe a repeating cycle-related pattern in attention, energy, emotional regulation, and executive functioning. Newer research is beginning to document these changes, especially in the premenstrual phase.
Estrogen rises in the first half of the cycle, called the follicular phase. It peaks around ovulation. Then estrogen drops in the second half of the cycle, called the luteal phase, while progesterone becomes more dominant.
For many ADHD women, the follicular phase feels more functional.
Then, in the week or two before menstruation, ADHD symptoms may intensify.
You may notice:
This is sometimes described as premenstrual ADHD worsening. It is different from PMS, although the two can overlap.
For some ADHD women, the premenstrual change is not only about mood. They also describe more difficulty with focus, working memory, task initiation, sensory tolerance, and managing daily demands.
If you have ever felt like a completely different person in the week before your period, this may be part of the reason.
Tracking your cycle alongside your ADHD symptoms can be very useful. It does not eliminate the pattern, but it helps you see it clearly.
It can help you:
Your hardest week is not proof that you are failing. It may be a predictable pattern that needs support.
Learn more about ADHD and your period here
ADHD and PMDD
Premenstrual Dysphoric Disorder, or PMDD, involves severe premenstrual mood and physical symptoms that cause meaningful impairment and improve after menstruation begins. A diagnosis is usually based on the timing and pattern of symptoms across the cycle, not on one difficult week.
Newer research suggests an important overlap with ADHD. In a 2025 cross-sectional study of 715 participants ages 18 to 34, possible PMDD identified by a screening tool was more common in participants with self-reported ADHD or high ADHD symptom levels than in the non-ADHD group. Because this was a screening study, it does not tell us that those participants all had a confirmed PMDD diagnosis. Read the 2025 study.
A 2026 study also found substantially greater premenstrual symptom burden and functional interference in the ADHD group. These studies support taking premenstrual worsening seriously while the research on the underlying mechanisms continues to develop. Read the 2026 study.
In lived experience and anecdotal reports, many women with ADHD describe a predictable premenstrual period when attention, emotional regulation, energy, sensory tolerance, sleep, or executive functioning becomes harder. That pattern can be important even when it does not meet criteria for PMDD.
PMDD can include marked irritability, depressed mood, anxiety or tension, difficulty concentrating, feeling overwhelmed or out of control, physical symptoms, and significant interference with work, relationships, or daily functioning. Suicidal thoughts can also occur and require prompt clinical attention.
If you suspect PMDD, prospective symptom tracking across cycles can help a qualified clinician distinguish PMDD from ordinary premenstrual worsening, depression, anxiety, or ADHD symptoms that fluctuate for other reasons.
Treatment is individualized. Evidence-based PMDD treatment can include SSRIs and, for some people, hormonal treatment prescribed specifically for PMDD. ADHD treatment may also need review if you notice a reliable cycle-related change, but stimulant dose changes should be discussed with your prescriber rather than made on your own.
For a deeper look at the overlap, tracking, and treatment questions, see ADHD and PMDD.
ADHD in Perimenopause and Menopause
Perimenopause is the transition leading up to menopause. Hormone levels can become more variable during this stage, while sleep, hot flashes, mood changes, caregiving demands, work stress, and other changes can also affect attention and executive functioning.
Clinically and anecdotally, many women describe reaching perimenopause and finding that strategies they relied on for years no longer work as well. Some seek ADHD assessment for the first time during this period. Newer research is beginning to support an association between ADHD symptoms and more difficult menopausal experiences, although the direction and mechanisms are still being studied. Read the 2025 menopause study.
A 2026 study also found greater menopausal symptom severity in the ADHD group than in the comparison group. Because these studies are observational, they cannot show that estrogen changes directly cause ADHD symptoms to worsen. Read the 2026 study.
This does not mean ADHD suddenly begins in perimenopause. More often, women describe a longstanding pattern that becomes harder to compensate for when sleep, cognitive load, hormonal change, stress, or other demands shift.
You may notice more difficulty with focus, memory, emotional regulation, overwhelm, fatigue, sleep, stress tolerance, or task initiation. Those changes can come from more than one source, so it is useful to look at the whole picture rather than assuming every new difficulty is either ADHD or menopause.
HRT is not an established treatment for ADHD itself. Some women report changes in ADHD functioning when menopausal symptoms are treated, but ADHD-specific evidence on HRT is still limited. HRT decisions should be based on your overall menopausal symptoms, medical history, risks, and preferences with an appropriate prescriber.
For more detail, see ADHD and Menopause in Women and ADHD and HRT.
ADHD Postpartum
The postpartum period combines a major hormonal transition with sleep disruption, physical recovery, frequent task switching, new responsibilities, and less control over routine. For an ADHD brain, that combination can change capacity quickly.
Newer research suggests that postpartum mental-health difficulties may be more common in women with ADHD. In a 2026 cross-sectional study, the ADHD group reported higher retrospective postpartum-depression scores than the comparison group. Because the study relied on retrospective self-report, it does not tell us that ADHD or hormone changes caused the difference, but it supports closer attention to postpartum mental health in ADHD women. Read the 2026 study.
In lived experience and anecdotal reports, women often describe more difficulty with organization, working memory, emotional regulation, sleep, and keeping up with repetitive daily tasks after a baby arrives. Hormonal changes may be part of the picture, but so are sleep loss, recovery, feeding demands, reduced downtime, and the sudden increase in things that have to be remembered.
Useful support may include:
- protecting sleep where possible
- externalizing routines and reminders
- reducing household and decision load
- sharing tasks explicitly rather than relying on one person to track everything
- screening and follow-up for postpartum depression or anxiety
- planning ADHD medication with a prescriber who can consider pregnancy or breastfeeding context
Medication decisions during pregnancy and breastfeeding are individualized. They should weigh the known and uncertain medication risks against the effects of untreated ADHD and the person's actual level of impairment. Stopping medication automatically is not the only possible approach, and medication changes should be made with a qualified prescriber.
For more detail, see ADHD and Postpartum Depression, ADHD and Postpartum Anxiety, and ADHD and Pregnancy.
What This Means for Treatment
The hormonal dimension of ADHD in women has practical implications for treatment.
Medication can feel different across the cycle
Anecdotally, some women report that stimulant medication feels less effective during the premenstrual phase. Research on cycle-related medication response is still limited, although newer reviews identify it as an important treatment gap.
If you notice a reliable pattern, track it and bring it to your prescriber. Some clinicians may consider individualized adjustments, but there is not yet a standard cycle-based ADHD medication protocol, and dose changes should not be made without medical guidance.
Hormonal treatment may be relevant for some women
PMDD and menopausal symptoms have their own evidence-based treatment options, which can include hormonal approaches for some people. Treating those conditions may change overall functioning, but hormonal treatment should not be presented as an established treatment for ADHD itself.
If HRT or hormonal contraception is being considered, the decision belongs in a medical conversation that includes your symptoms, health history, risks, preferences, and the reason the hormone treatment is being used.
Non-medication support matters
Medication is only one part of ADHD treatment.
During postpartum, perimenopause, or the luteal phase, other supports may become even more important.
These may include:
- simpler routines and fewer unnecessary decisions
- reduced demands during lower-capacity periods
- external reminders and clearer written information
- support with meals, household tasks, or other recurring work
- more recovery time
- clear communication with family or partners about what is harder and what would help
Cycle tracking is useful clinical information
You may want to track:

Tracking your menstrual cycle and ADHD symptoms can help you see patterns.
This information can help you make better decisions about scheduling, workload, medication conversations, and support.
Providers need to understand both ADHD and hormonal health
Finding providers who understand both ADHD and women’s hormonal health is harder than it should be.
You may need to be the person connecting the dots.
That is not fair. But knowing what to ask for makes advocacy easier.
The Flourish Model and Hormonal Transitions
Hormonal changes are a good example of why ADHD support has to account for fluctuating capacity. I use the Flourish Model to help women notice their own patterns, reduce self-blame, adjust workload and expectations when symptoms change, bring clearer questions to medical providers, and protect sleep and recovery.
Tracking what becomes harder before your period, postpartum, or during perimenopause can turn an unpredictable experience into useful information for planning and treatment. Read about the full Flourish Model for ADHD women.
Frequently Asked Questions
For some women, yes. Newer research suggests ADHD symptoms can vary across menstrual and reproductive stages, but the mechanisms are still being studied and the pattern is not the same for everyone. In lived experience and anecdotal reports, women often report changes before menstruation, postpartum, or during perimenopause.
Perimenopause can bring hormonal variability, sleep disruption, mood changes, and other demands that may make longstanding ADHD difficulties harder to compensate for. Newer observational research supports an association between ADHD symptoms and more difficult menopausal experiences, but it does not prove that estrogen decline directly causes ADHD symptoms to worsen.
Probably, but the evidence is still developing. A 2025 study found higher rates of possible PMDD on a screening measure among participants with ADHD or high ADHD symptom levels. A positive screen is not the same as a confirmed PMDD diagnosis, which is why prospective cycle tracking and clinical assessment are important.
Many ADHD women report more difficulty with focus, working memory, emotional regulation, sleep, energy, or task initiation during the premenstrual phase. Newer research supports cycle-related symptom changes, but there is not yet one proven biological explanation. Hormonal change may interact with ADHD-related brain systems alongside sleep, pain, stress, mood, and other factors.
Newer research suggests women with ADHD may experience more postpartum mood difficulty, although the reasons are likely multifactorial. Hormonal change, sleep loss, recovery, increased cognitive load, reduced routine, and pre-existing mental-health risks may all contribute. Planning ADHD treatment and postpartum support with your medical team can be useful.
The Bigger Picture
For too long, the hormonal dimension of ADHD in women has been missed.
Women were told their symptoms were PMS, stress, anxiety, motherhood, or normal aging. The ADHD piece was missed. The hormone piece was missed. The interaction between the two was missed.
That left many women trying to manage real changes in brain function without language, treatment, or support.
This is changing, slowly.
More research is being done. More providers are learning about ADHD in women. More women are recognizing the pattern and bringing better questions to their care teams.
You deserve care that accounts for your ADHD, your hormonal biology, and the way the two interact across your lifespan.
Continue Exploring
- ADHD in Women — the complete picture
- ADHD and PMDD
- ADHD and HRT
- Dopamine and ADHD
- ADHD and Sleep
- ADHD and Anxiety
- ADHD Burnout in Women
- ADHD Sensory Overload
- ADHD and Eating Disorders
- ADHD and the Menstrual Cycle
- ADHD and Menopause
- ADHD and Pregnancy
- ADHD and Migraines in Women
If you are a woman with ADHD navigating the hormonal dimension of your symptoms, I offer neurodivergent-affirming therapy and support via telehealth in North Carolina and South Carolina. I bring 31 years of clinical experience and a deep understanding of how ADHD actually shows up in women's lives — including the parts that most providers miss.
Work with Kristen McClure | Learn more about neurodivergent-affirming support
Ready to Work Together?
If what you've read here feels familiar, I'd love to hear from you. I work with women with ADHD across North Carolina and South Carolina via secure telehealth — from wherever you are in either state.
